omniVUE Intelligence for Healthcare Operations
Predict demand. Build better schedules. Respond before the shift breaks.
Bring workforce demand, availability, skill mix, scheduling rules and live operational pressure into one human-supervised decision environment.
Health-system operations · Workforce logistics · Clinical leaders · Scheduling teams
01
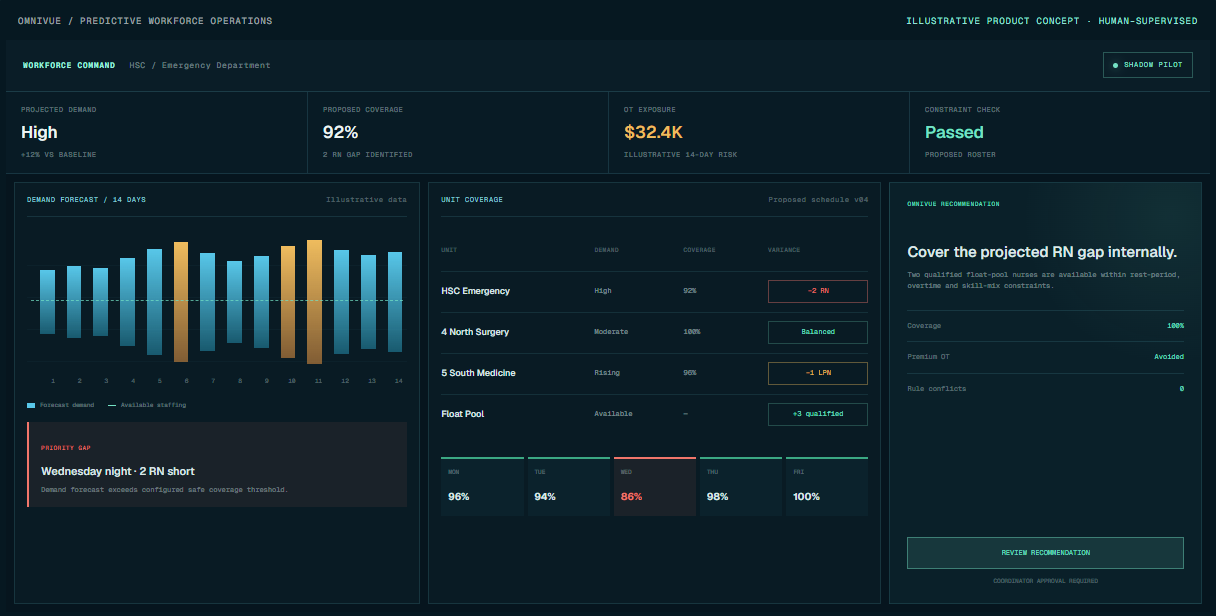
Forecast staffing pressure before the shift
02
Generate schedules around demand and constraints
03
Respond to call-ins without losing the system view
04
Measure the opportunity in a shadow pilot
The operational challenge
Static rosters meet a health system that never stands still.
Patient demand changes, staff call in sick, beds lock, qualifications matter and every coverage decision is shaped by policy, availability and collective agreements. The result is often a last-minute search for coverage when the most expensive options are the only ones left.
omniVUE Intelligence is being designed to help teams model that complexity earlier—without handing scheduling authority to an algorithm.
Flagship capability
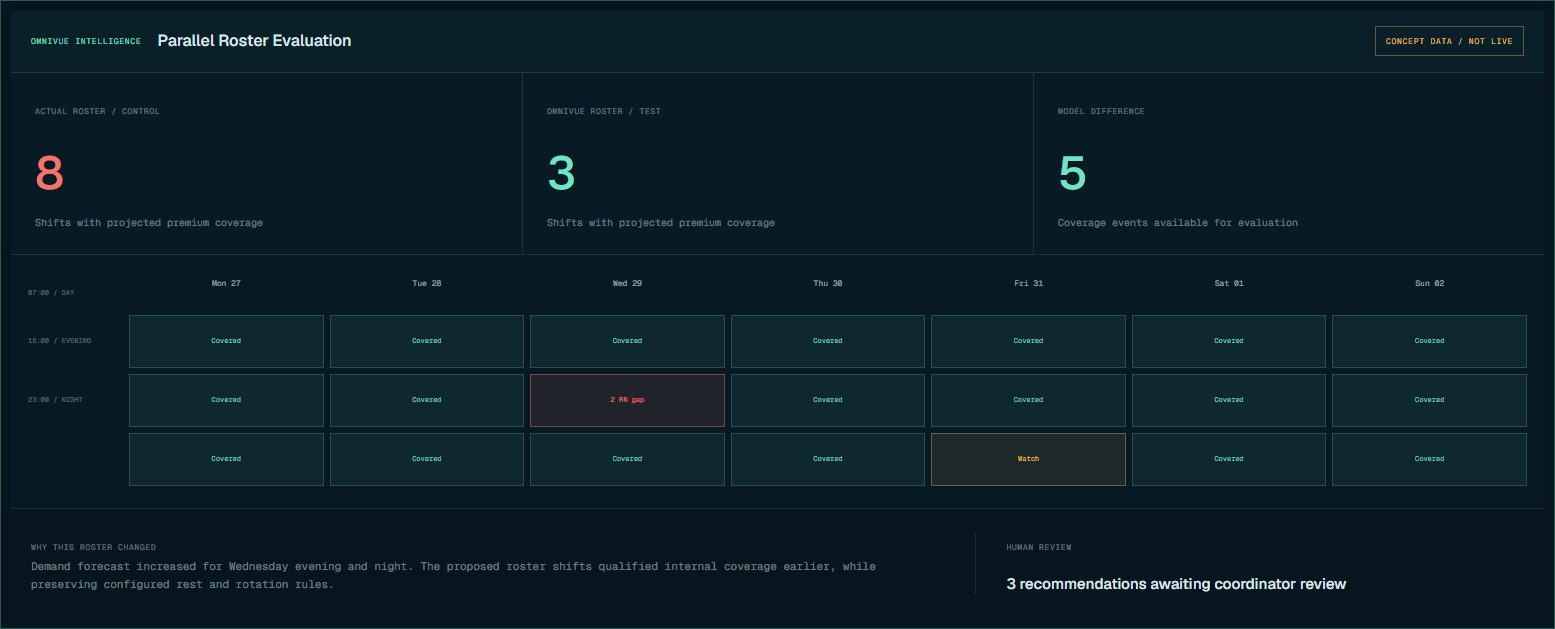
From predicted demand to a constraint-aware roster.
Forecast the workforce requirement, generate a proposed schedule, explain how each constraint was applied and help coordinators act earlier when reality changes.
Proposed capability · Illustrative data · Coordinator approval required
01
Forecast demand
Model expected census, acuity and operating pressure from historical and current signals.
02
Build the roster
Generate a proposed skill mix around staffing requirements, availability, leave and local rules.
03
Test every constraint
04
Respond to change
05
Keep people in control
HEALTHCARE OPERATIONS INTELLIGENCE
Start with workforce planning.
Expand around the operational system.
01 / Flagship pilot
Predictive workforce operations
Forecast unit demand, generate constraint-aware schedules and respond to staffing exceptions before premium coverage becomes the default.
02 / Current demonstrator
Patient flow & system coordination
Connect facility pressure, transfer options, transport availability, routes and governed response across the regional network.
03 / Proposed concept
Triage operations support
Help clinical teams organize queues, identify reassessment risk and coordinate routing using approved rules—without replacing clinical judgment.
PROPOSED TRIAGE OPERATIONS CONCEPT
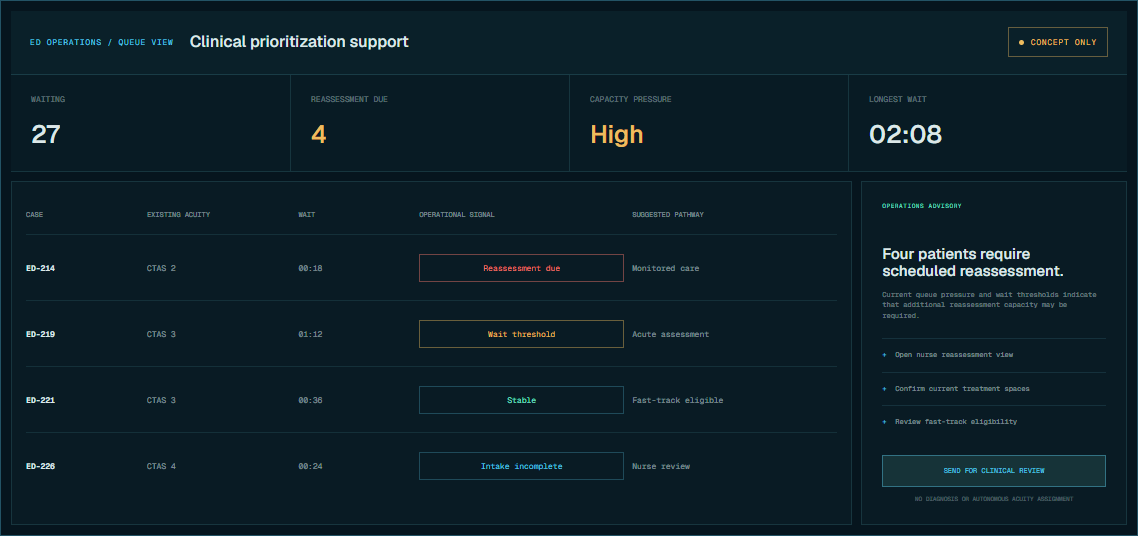
Help clinical teams see who may need attention next.
A triage operations workspace could organize the existing queue, highlight wait and reassessment thresholds, connect patients to available care pathways and bring emerging pressure to a clinician's attention.
Decision support only · No diagnosis · No autonomous clinical prioritization
01
Uses established clinical inputs
The concept begins with clinician-entered acuity, approved protocols and available operational data—not unconstrained AI judgment.
02
Surfaces operational risk
Flag elapsed time, missing intake information, reassessment thresholds and capacity pressure for human review.
03
Preserves clinical authority
Nurses and physicians retain responsibility for acuity, diagnosis, routing and patient-care decisions.
A WORKING HEALTHOPS FOUNDATION
Patient-flow coordination is already visible in the platform.
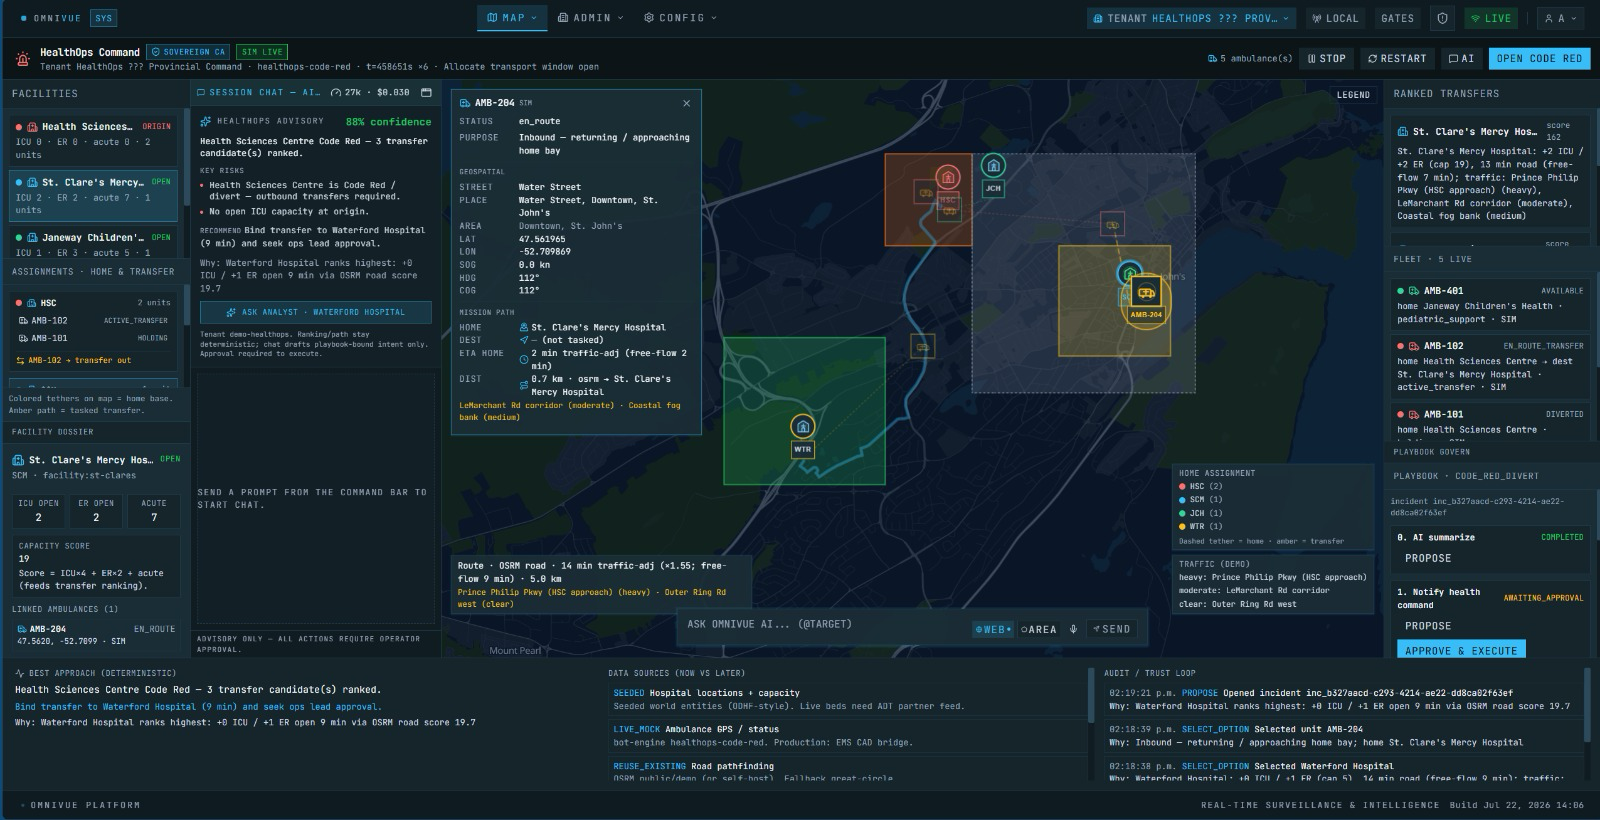
The current St. John’s demonstrator connects facility pressure, ranked transfer destinations, ambulance context, routes, an AI-assisted summary and an approval-gated operational playbook.
The demonstrator supports operational coordination. It is not an EHR or EMR and does not provide clinical diagnosis.
A low-disruption first engagement
Prove the workforce opportunity without changing a live schedule.
A 90-day parallel shadow pilot compares omniVUE’s proposed roster against the actual schedule while existing staffing authority and processes remain unchanged.
01 / Days 01–30
Data & rule configuration
Connect agreed historical datasets, define the pilot unit and translate workforce policies and collective-agreement constraints into testable rules.
02 / Days 31–60
Parallel shadow operation
Run the proposed roster alongside the actual schedule without changing live assignments. Record call-ins, gaps, coverage decisions and cost triggers.
03 / Days 61–90
Comparative evaluation
Compare the two approaches across coverage, overtime exposure, agency reliance, administrative effort, rule compliance and preference matching.
DESIGNED FOR CANADIAN HEALTH-SYSTEM CONTROL
Operational intelligence that fits the governance model.
A deployment would be configured around customer data residency, privacy, organizational roles, collective agreements and approval authority. omniVUE works as an operational layer—not a replacement for clinical or workforce record systems.
CONFIGURED INPUTS
A focused path to a saleable pilot
Start with one unit, one scheduling problem and ninety days of evidence.
Select a high-variability unit, agree on the rules and evaluation measures, then compare the actual roster with omniVUE's proposed schedule in a controlled shadow environment.

Canadian-built software for complex operational environments.
PO Box 1506, Station C
St. John's, NL
A1C 5N8
Canada
© 2026 ENGAGE CREATIVE TECHNOLOGIES